




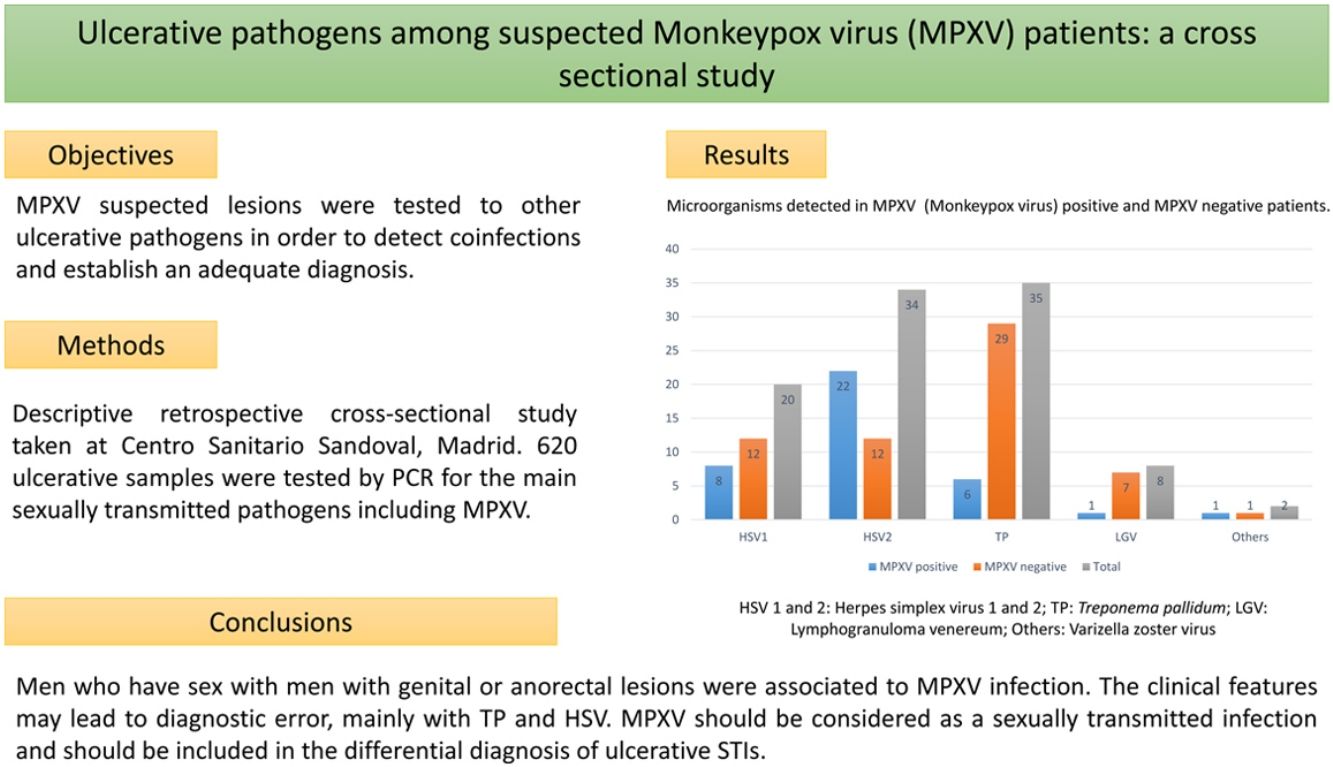
MPXV suspected lesions were tested to other ulcerative pathogens in order to detect coinfections and establish an adequate diagnosis. Descriptive retrospective cross-sectional study taken at Centro Sanitario Sandoval, Madrid. Six hundred twenty ulcerative samples were tested by PCR for the main sexually transmitted pathogens including MPXV. A multivariate analysis was carried out to determine factors associated to MPXV. We detected 447 samples positive for MPXV, 38 of them were also positive for some of the other pathogens, mainly herpes simplex virus type 2 (HSV2). In the MPXV samples, 35.3% (61 of 173) of them were positive for ulcerative pathogens, mainly Treponema pallidum (TP). Men who have sex with men with genital or anorectal lesions were associated to MPXV infection. The clinical features may lead to diagnostic error, mainly with TP and HSV. MPXV should be considered as a sexually transmitted infection and should be included in the differential diagnosis of ulcerative STIs.

Humans’ infection with MPXV was first reported in the Democratic Republic of Congo in 1970.1 In May, 2022, the first cases of the multinational outbreak were reported in Europe,2 prompting the WHO to declare the epidemic a public health emergency of international concern in July, 2022.3 As of 31 July 2024, a total of 102997 laboratory confirmed cases, including 223 deaths, have been reported to WHO.4 On 14 August 2024, WHO declared MPXV a public health emergency of international concern due to the risk of international expansion of the new clade Ib.5 The 2022 outbreak has been primarily associated with close intimate contact (including sexual activity) and most cases have been diagnosed among men who have sex with men.6–8 Sexual transmission has been suspected from the beginning of outbreaks, mainly with the appearance of cases related with severe anal pain, proctitis9 and genital ulcers.10–12 In addition, the presence of another concomitant sexually transmitted pathogens in patients reveal the possibility of sexual transmission.13,14
The aim of this study was to determine STI ulcerative coinfections in MPXV positives ulcers and to identify other ulcerative pathogens in MPXV negative ulcers, to enhance the importance of an adequate differential diagnosis.
Epidemiological, clinical and microbiological characteristics from suspected patients were studied to determine risk factors associated to MPXV.
Material and methodsDescriptive retrospective cross-sectional study taken at Centro Sanitario Sandoval, sexually transmitted infections clinic in Madrid. Between May and November 2022, a total of 620 ulcer samples from MPXV suspected patients (one sample per patient) who were attended with ulcerative lesions consistent with MPXV infection, were collected for MPXV detection. Posteriorly we determined the presence of other ulcerative pathogens in order to detect coinfections or other ulcerative STIs. Ulcerative pathogens other than MPXV were detected by RT-PCR Seegene Allplex® Ulcer Assay (Seegene, South Korea). The nucleic acid extraction was carried out in Microlab STARlet-Hamilton (Seegene) and RT-PCR in CFX96 Touch Real-Time (Bio-Rad). The presence of MPXV in the samples was determined in the Reference Laboratory (National Microbiology Center, Majadahonda, Madrid, Spain) or in the Microbiology Laboratory of Hospital 12 de Octubre, Madrid, Spain. Epidemiological, clinical and microbiological characteristics were obtained from the review of the medical histories.
Statistical analysisThe qualitative variables are shown with their frequency distribution. The quantitative variables are summarized with the average and standard deviation or with the median and interquartile range if they do not fit within a normal distribution.
The association between qualitative variables was carried out using the chi-squared test or Fisher's exact test, if necessary. Odds ratios were performed to quantify the strength of the crude association between qualitative dichotomous variables.
For quantitative variable comparison, the Student's t-test (two groups) or analysis of variance (ANOVA; if more than two groups) or their non-parametric equivalents were used.
A logistic regression model was adjusted with the objective of identifying the factors that are independently associated with the presence of MPX in the ulcers. The factors that were introduced in the logistic regression model were those that presented a p<0.10 in the bivariate analyze and/or clinical relevancy. A significance level of 5% was accepted for all variables. The processing and analysis of the data was done using IBM SPSS statistical package, version 26.0.0.0.
ResultsEpidemiological, behavioral and microbiological characteristics of patientsMost of suspected patients were male (98.9%), mainly men who have sex with men (MSM). Median age was 36.55 years. Fifty of them were sex workers (8.1%) and 3.4% of the total patients used injected drugs. Eighty-seven (14%) were people living with HIV (PLHIV). 37.9% of the patients were HIV pre-exposure prophylaxis (PrEP) users.
38.5% of ulcers analyzed were genital and 31% anorectal. Rest of them, 22.6% cutaneous and 7.9% oropharyngeal.
Differences between MPXV positive (MPXV+) and MPXV negative (MPXV−) patients. MPXV infection risk factorsA total of 447 tested positive for MPXV. The average age was just the same for both groups. Only one woman was positive to MPXV among positives patients, 446 were men. We observed 3 heterosexual patients positive to MPXV. The rest, 444 were MSM. The main location from MPXV+ patients were genital and anorectal ulcers (180 and 149 respectively), being genital and cutaneous more frequently in MPXV− patients. Twenty nine MPXV+ patients were sex workers and 21 on MPXV−. Fifteen MPXV+ and 6 MPXV− were intravenous drug users. Fifty sex patients (12.5%) MPXV+ were PLHIV. We observed 10% of MPXV+ patients with another STI such as Neisseria gonorrhoeae (NG) (19 patients), CT (10), MG (9), and 7 patients mixed infections.
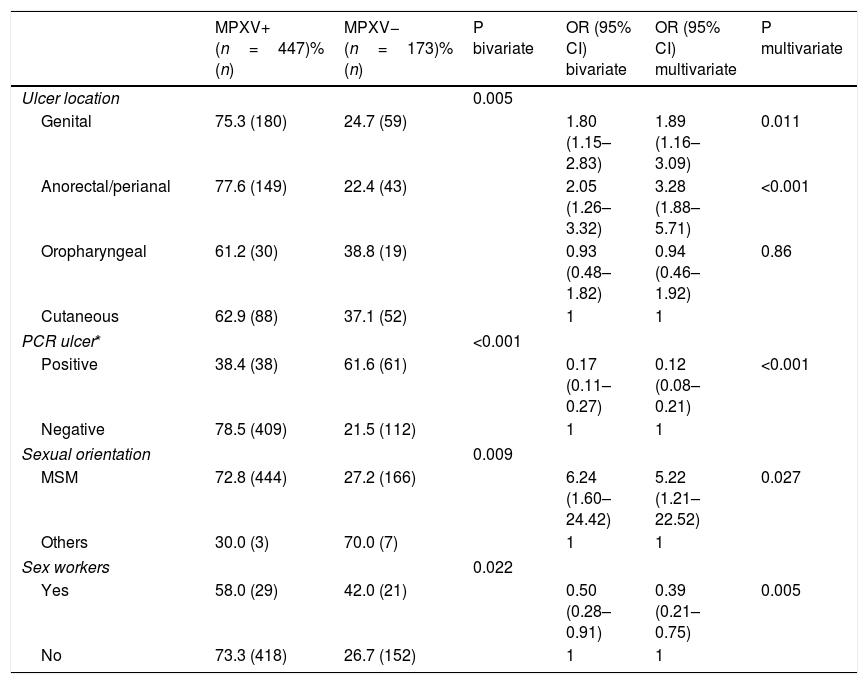
An analysis was performed the determine factors associated with the presence of MPXV infection (Table 1).
Analysis of the factor associated with the presence of MPXV (n=620).
| MPXV+ (n=447)% (n) | MPXV− (n=173)% (n) | P bivariate | OR (95% CI) bivariate | OR (95% CI) multivariate | P multivariate | |
|---|---|---|---|---|---|---|
| Ulcer location | 0.005 | |||||
| Genital | 75.3 (180) | 24.7 (59) | 1.80 (1.15–2.83) | 1.89 (1.16–3.09) | 0.011 | |
| Anorectal/perianal | 77.6 (149) | 22.4 (43) | 2.05 (1.26–3.32) | 3.28 (1.88–5.71) | <0.001 | |
| Oropharyngeal | 61.2 (30) | 38.8 (19) | 0.93 (0.48–1.82) | 0.94 (0.46–1.92) | 0.86 | |
| Cutaneous | 62.9 (88) | 37.1 (52) | 1 | 1 | ||
| PCR ulcer* | <0.001 | |||||
| Positive | 38.4 (38) | 61.6 (61) | 0.17 (0.11–0.27) | 0.12 (0.08–0.21) | <0.001 | |
| Negative | 78.5 (409) | 21.5 (112) | 1 | 1 | ||
| Sexual orientation | 0.009 | |||||
| MSM | 72.8 (444) | 27.2 (166) | 6.24 (1.60–24.42) | 5.22 (1.21–22.52) | 0.027 | |
| Others | 30.0 (3) | 70.0 (7) | 1 | 1 | ||
| Sex workers | 0.022 | |||||
| Yes | 58.0 (29) | 42.0 (21) | 0.50 (0.28–0.91) | 0.39 (0.21–0.75) | 0.005 | |
| No | 73.3 (418) | 26.7 (152) | 1 | 1 | ||
MPXV+: mpox virus positive patients; MPXV−: mpox virus negative patients; OR: odds ratio; CI: confidence interval.
Ulcer location was an important predictor of MPXV infection, with genital (OR: 1.8; p value: 0.011) and anorectal (OR: 3.28; p value: <0.001) lesions being statistically significant in comparison with cutaneous ulcers.
The presence of others ulcerative pathogens at the same ulcer (PCR ulcer, OR: 0.12; p value: <0.001) decrease the possibility to have a MPXV infection even in multivariate analysis.
MSM were the main population at risk of suffering an infection with MPXV in our study.
In addition, sex workers had less probability to acquire MPXV infection than the rest of population.
In our study population, we found that MSM with genital or anorectal lesions had more probability to suffer MPXV infections, unlike those who had other positive ulcerative pathogen and were sex workers.
Detection of ulcerative pathogens other than MPXVWe detected 99 (16%) samples positives for ulcerative pathogens. It was observed that 8.5% (38 of 447) of the MPXV+ samples were also positive for some of the other pathogens. In the MPXV− group, this percentage increased significantly, reaching 35.3% of the total MPXV− samples (61 of 173). Treponema pallidum (TP) was the principal ulcerative pathogen (35, 5.6% of total sample analyzed), mainly in MPXV negative samples (n=29). The second microorganisms detected was herpes simplex virus type 2 (HSV2) (n=34, 5.5% of total samples analyzed), especially among MPXV+ samples (n=22). Herpes simplex virus type 1 (HSV1) was also observed in both MPXV+ and MPXV− (n=8 and n=12, respectively). Eight cases of lymphogranuloma venereum (LGV) (7 cases among MPXV−) were detected. Coinfection MPXV-HSV2 was the most frequent coinfection observed among all samples.
Cycle threshold (Ct) was determined for each of the microorganisms. Ct median value was higher than 30 for HSV2 in both MPXV positive and negative. For the rest of microorganisms, the Ct median values were less than 30.
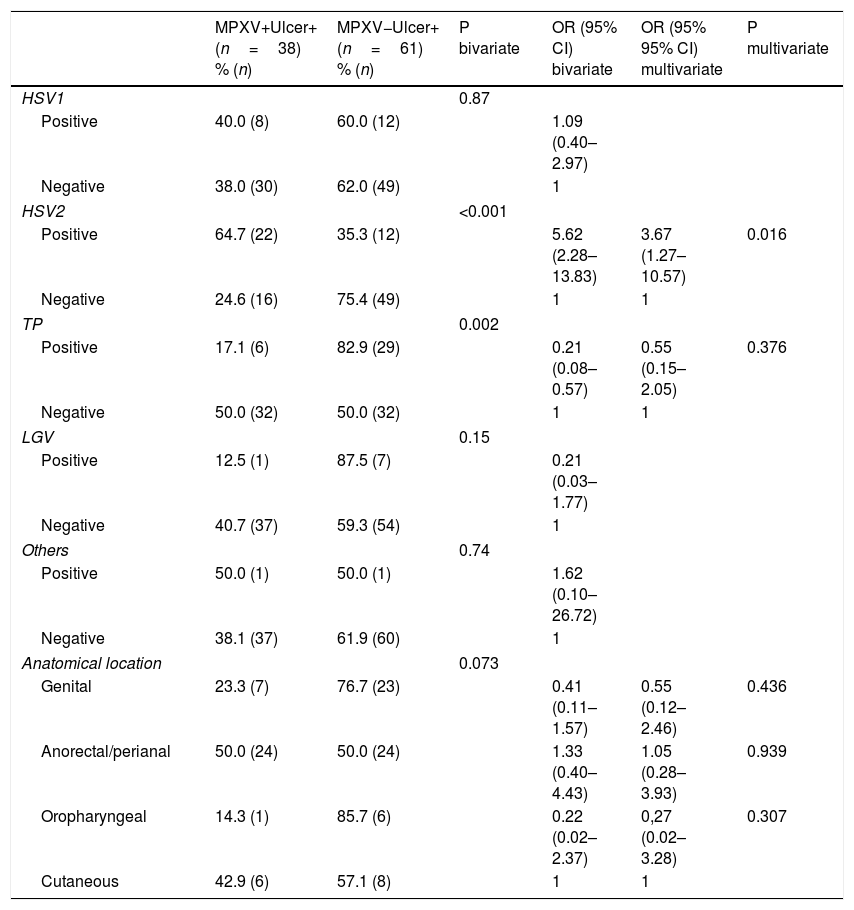
Among samples with positive ulcer PCR (99), we found more risk of HSV2 infection within MPXV+ patients (OR: 5.62; p=<0.001). On the other hand, MPXV− patients were more susceptibles to suffer TP infection (OR: 0.21; p=0.002). After multivariate analysis, HSV2 was still associated with MPXV+ coinfection. However, after multivariate analysis, the negative association between TP infection and MPXV infection among positive ulcer patients disappears. In the bivariate analysis there seemed to be a non-statistically significant tendency between anatomical location and the presence of coinfection, being the anorectal/perianal region the most probable location for coinfection. However, when adjusted by ulcerative pathogens (TP and HSV2), this association disappears (Table 2).
Analysis of the microorganisms detected and anatomical location of the ulcer among positive ulcer patients (n=99) and its association with MPXV.
| MPXV+Ulcer+(n=38) % (n) | MPXV−Ulcer+(n=61) % (n) | P bivariate | OR (95% CI) bivariate | OR (95% 95% CI) multivariate | P multivariate | |
|---|---|---|---|---|---|---|
| HSV1 | 0.87 | |||||
| Positive | 40.0 (8) | 60.0 (12) | 1.09 (0.40–2.97) | |||
| Negative | 38.0 (30) | 62.0 (49) | 1 | |||
| HSV2 | <0.001 | |||||
| Positive | 64.7 (22) | 35.3 (12) | 5.62 (2.28–13.83) | 3.67 (1.27–10.57) | 0.016 | |
| Negative | 24.6 (16) | 75.4 (49) | 1 | 1 | ||
| TP | 0.002 | |||||
| Positive | 17.1 (6) | 82.9 (29) | 0.21 (0.08–0.57) | 0.55 (0.15–2.05) | 0.376 | |
| Negative | 50.0 (32) | 50.0 (32) | 1 | 1 | ||
| LGV | 0.15 | |||||
| Positive | 12.5 (1) | 87.5 (7) | 0.21 (0.03–1.77) | |||
| Negative | 40.7 (37) | 59.3 (54) | 1 | |||
| Others | 0.74 | |||||
| Positive | 50.0 (1) | 50.0 (1) | 1.62 (0.10–26.72) | |||
| Negative | 38.1 (37) | 61.9 (60) | 1 | |||
| Anatomical location | 0.073 | |||||
| Genital | 23.3 (7) | 76.7 (23) | 0.41 (0.11–1.57) | 0.55 (0.12–2.46) | 0.436 | |
| Anorectal/perianal | 50.0 (24) | 50.0 (24) | 1.33 (0.40–4.43) | 1.05 (0.28–3.93) | 0.939 | |
| Oropharyngeal | 14.3 (1) | 85.7 (6) | 0.22 (0.02–2.37) | 0,27 (0.02–3.28) | 0.307 | |
| Cutaneous | 42.9 (6) | 57.1 (8) | 1 | 1 | ||
MPXV+Ulcer+: mpox virus and other ulcerative pathogen positive patients; MPXV−Ulcer+: mpox virus negative and other ulcerative positive patients; TP: Treponema pallidum; HSV1: herpes simplex virus type 1; HSV2: herpes simplex virus type 2; LGV: lymphogranuloma venereum; Ct: cycle threshold; OR: odds ratio; CI: confidence interval.
Demographic and epidemiological characteristics from our patients were similar to other studies in literature.2,7,8,15 Genital and anorectal ulcers were predominant lesions in MPXV+ patients, and were an important predictor for MPXV infection, as well as those who had a negative test for other ulcerative pathogens. These results highlight the need to choose preferably the ulcers in these anatomic sites instead of other locations to ensure the correct diagnostic of MPXV infection. It also highlights the importance of an intimate sexual contact considering this pathology as a new sexually transmitted infection, like other studies have suggested.13,14,16 According to this, 2022 MPXV outbreak has affected mainly men, particularly MSM with high-risk sexual behaviors, as we have observed in our multivariate study (p=0.027), corroborating sexual contact as one of the main routes of transmission. In our study we found that sex workers had less risk to acquire MPXV infection than the rest of the people (p=0.005). We think this could be due to a greater awareness of these population about the risk of transmission to their clients.
The high percentage of ulcerative pathogens detected in both MPXV+ and MPXV− patients suggests the need for complete screening of STI ulcerative pathogens in ulcer samples from MPXV suspected patients. The clinical features of the ulcer in these patients may lead to diagnostic error, mainly with TP and HSV2, so we must ensure a correct diagnosis of other STIs by requesting the study of other ulcerative pathogens. In the case of MPXV+ patients, we observed a strong association between MPXV and HSV2, even in the multivariate model, although the high Ct median value may suggest a recurrent infection rather than a primary one. For other pathogens, as HSV1, TP and LGV, Ct median values were less than 30, so we could consider active infections by these pathogens concomitantly with infection by MPXV. In all cases, its necessary detect and treat these pathogens to improve and resolve the patient's pathology and cutting the chains of transmission. For MPXV− patients, the association was strong with TP in the bivariate analysis, but disappear in multivariate. About TP, primary lesions can be difficult to differentiate clinically and may be confused with MPXV. Anyway, our results indicate the necessity to diagnose other ulcer pathogens and the difficulty in many cases of clinically differentiating an ulcerative lesion, even in a MPXV outbreak.
Our study has different limitations such as the population attended in our clinic (predominantly MSM), the lack of systematic collection of samples for the detection of other non-ulcerative STIs and the retrospective observation of epidemiological data.
All data provided in our study enhance the need to perform microbiological studies including other ulcerative sexually transmitted pathogens in MPXV suspected cases, in order to diagnose them properly. The clinical features of the ulcer in these patients may lead to diagnostic error, mainly with TP and HSV. Therefore, MPXV can be considered a STI, and it should be included in the differential diagnosis of ulcerative STIs, even in non-outbreak MPXV times and in the face of the growing threat of expansion of new clades across different continents. It should be clarified that this statement would not be applicable to the global MPXV outbreak, especially in the African outbreak of 2024, where transmission patterns are different from those observed in the rest of the world.
Ethical approvalIt was approved by the ethics committee of Hospital Clinico San Carlos in Madrid with internal code: 22/614-E.
FundingThis study has no financial funding.
Conflict of interestThere is no conflict of interest.




