







Mucous membrane pemphigoid (MMP) is a heterogeneous group of chronic blistering diseases that primarily affects the mucous membranes.1 It is characterized by the presence of various autoantibodies directed against the basement membrane: BP180, BP230, α6β4 integrin, laminin 332, and collagen VII.1 The specific phenotype–antigen relationship remains to be elucidated, although certain associated prognostic factors have been identified. We describe the specific autoantibody profile identified in a case series of MMP and its correlation with the literature.
We conducted a single-center, retrospective, descriptive observational study including all cases diagnosed with MMP from February 2020 through February 2024. Autoantibodies were studied by Dr. Takeshi Hashimoto in Osaka, Japan. The serum study included indirect immunofluorescence on normal skin (IIF) and NaCl-split skin (ss-IIF), immunoblotting (IB), and ELISA (Fig. 1).

Results of case report #3. Clinical image, indirect immunofluorescence on normal skin (IIF) and NaCl-split skin (ss-IIF), and immunoblotting (IB). (A) Clinical image showing desquamative and erosive lower perialveolar gingivitis, as well as oral and gingival mucosal synechiae with loss of the lingual frenulum. (B) Standard IIF and ss-IIF images: standard IIF shows IgA deposition along the basement membrane zone (BMZ); ss-IIF shows IgG and IgA deposition on the epidermal roof. (C) IB images performed on the patient's serum, showing positive IgG reactivity on IB of concentrated HaCaT cell culture supernatant (120-kDa LAD-1), BP230, and hemidesmosome-rich (HD) fraction for anti-β4 integrin antibodies. IgG and IgA reactivity on IB for 190-kDa periplakin may represent nonspecific reactivity, as normal serum also shows this band. Conclusion of the circulating antibody study performed by Dr. Hashimoto, Osaka, Japan: these results – positive IgG and IgA reactivity on IIF and variable reactivities with BP180 – suggest the diagnosis of anti-BP180-type MMP. Although the main epitope in anti-BP180-type MMP is located in the C-terminal region of BP180, this case tested negative for the recombinant C-terminal BP180 protein. The reason for this finding is unknown. However, the serum showed IgG antibodies against 120-kDa LAD-1, which corresponds to the ectodomain of BP180. In addition, the reason for the inconsistent results observed for antibodies against the BP180 NC16A domain between IB and ELISA, as well as for BP230 between both techniques, is unknown; positive ELISA results for BP180 are not shown in the figure. This discrepancy may be attributable to differences in methodology. Anti-integrin β4 IgG antibodies were also weakly positive, although the significance of this finding is currently unknown, as these antibodies may be detected in several types of MMP. Finally, based on the clinical features, this case was considered oral anti-BP180-type MMP, specifically LAD-1 type, with IgG and IgA anti-BMZ antibodies.
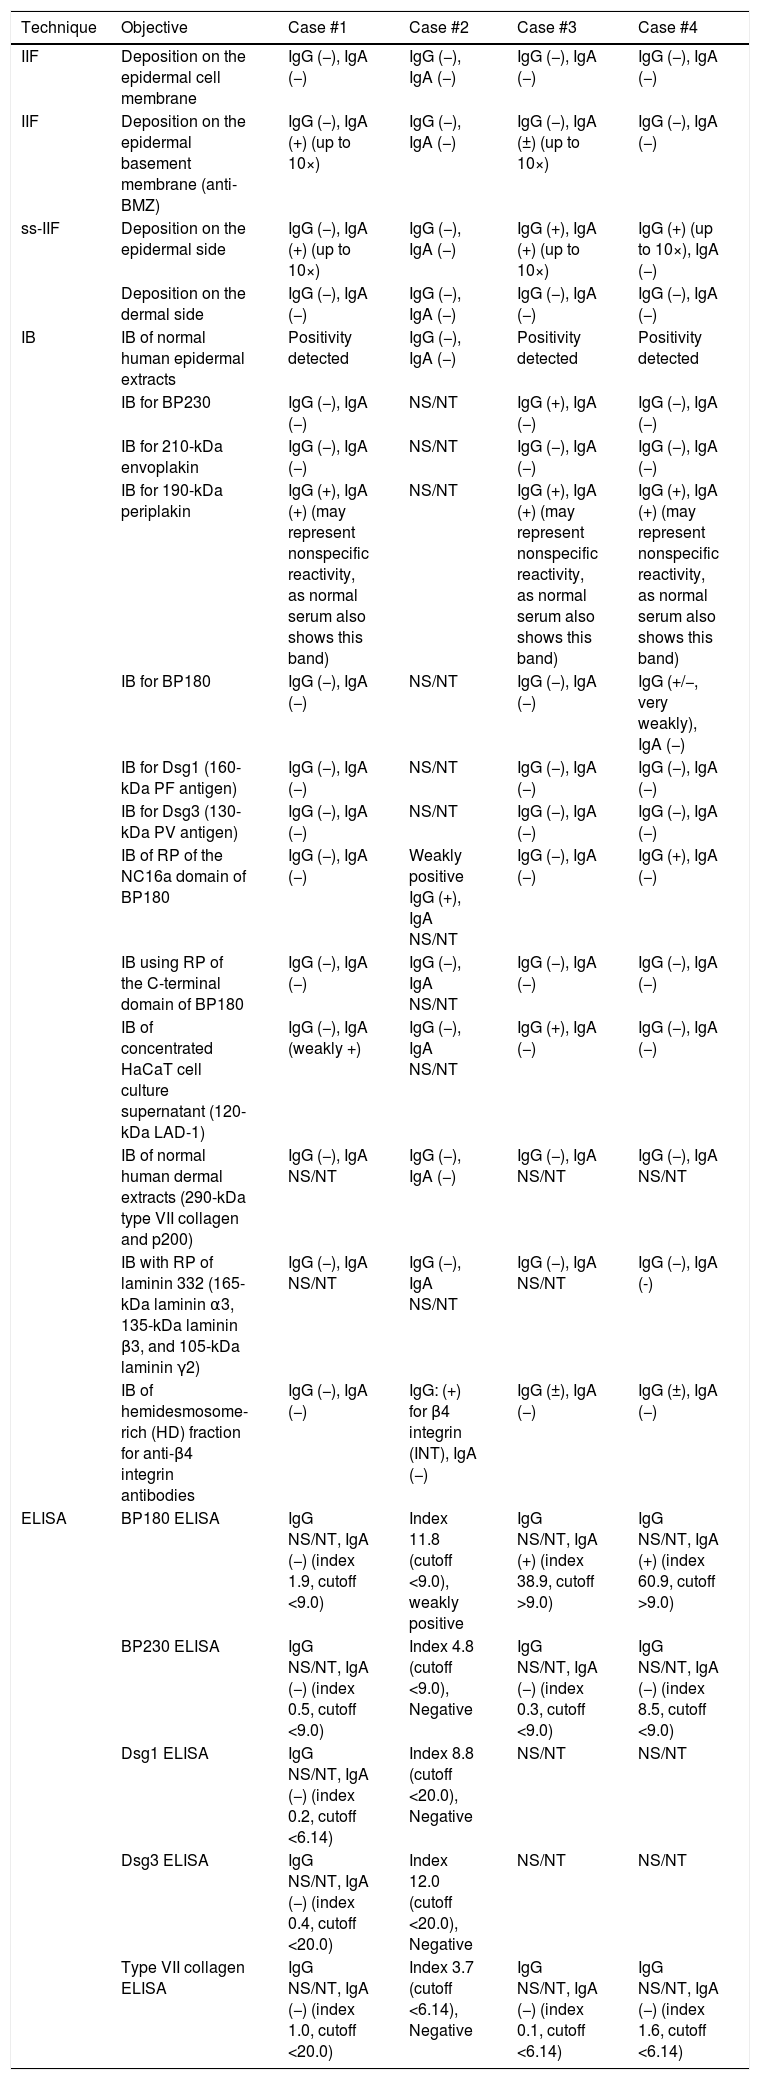
A total of 4 patients were included; their clinical and serological characteristics are shown in Table 1, Table 2, and Supplementary data 1.
Clinical, diagnostic, and therapeutic details of MMP cases.
| Case | Sex/age | Location/MMPDAI/disease duration | DIF | Conclusion of circulating serum autoantibody study by IIF, salt-split skin IIF, IB, and ELISA | Diagnosis | Treatment administered | Clinical course |
|---|---|---|---|---|---|---|---|
| 1 | F/76 | Oral ocular cutaneousMMPDAI A: 24/250 D: 8/125 years | Linear deposition of IgG and C3 along the basement membrane. | • IIF and salt-split skin IIF: o IgA on the epidermal side• IB:○ Weakly positive IgA against 120-kDa LAD-1, corresponding to the C-terminal half of BP180○ Negative for integrin β4 for both IgG and IgA• ELISA:○ Negative | Predominantly ocular MMP with anti-BP180 IgA antibodies against LAD-1±IgG. | IV immunoglobulinsIV rituximabIV cyclophosphamideOral sulfasalazineOral cyclosporineOral prednisone | • Resolution of mucosal lesions.• Remission after treatment with cyclophosphamide, sulfasalazine, and rituximab.• Cicatricial ocular synechiae.• Atrophic cutaneous scars with milia cysts. |
| 2 | M/68 | Oral esophageal nasopharyngeal ocular cutaneousMMPDAI A: 32/250 D: 10/1220 years | Linear deposits of IgG and C3 along the dermoepidermal basement membrane. | • IIF and salt-split skin IIF:○ Negative• IB:○ Weakly positive IgG against the BP180 NC16A domain○ Positive IgG against integrin β4• ELISA:○ Positive for BP180 | Multisite MMP with anti-BP180 IgG antibodies against NC16A and anti-integrin β4 IgG antibodies. | IV immunoglobulinsIV rituximabIV cyclophosphamideOral mycophenolate mofetilOral cyclosporineOral dapsoneOral prednisone | • Complete remission of cutaneous bullous lesions, with residual scarring, as well as mucosal lesions after cyclophosphamide and rituximab.• Esophageal stenosis requiring balloon dilation.• Mild ocular cicatricial symblepharon. |
| 3 | M/62 | OralMMPDAI A: 12/250 D: 0/123 years | Linear deposits of C3, IgG, and IgA along the basement membrane. | • IIF and salt-split skin IIF:○ IgA and IgG on the epidermal side• IB:○ Positive IgG against the BP180 LAD-1 domain○ Weakly positive IgG against integrin β4; significance unknown○ Weakly positive IgG against BP230; significance unknown• ELISA:○ Positive for IgA against BP180 | Oral MMP with anti-BP180 IgG and IgA antibodies against LAD-1. | Oral dapsoneOral cyclosporineIV immunoglobulinsOral sulfasalazineSC methotrexateOral prednisoneIV rituximab | • Lack of efficacy of first-line therapies, with persistent erosive lesions of the oral mucosa.• Good response to IV rituximab. |
| 4 | F/67 | Cutaneous involvement: Brunsting-Perry pemphigoidMMPDAI A: 8/250 D: 2/122 years | Granular deposits of IgG, IgA, and C3.* | • IIF and salt-split skin IIF:○ IgG on the epidermal side• IB:○ Positive IgG against the BP180 NC16A domain○ Weakly positive IgG against integrin β4; significance unknown• ELISA:○ Positive for IgA against BP180 | Brunsting-Perry MMP with anti-BP180 IgG and IgA antibodies against NC16A. | Oral dapsoneSC methotrexateOral prednisoneIV rituximab | • Lack of efficacy of first-line treatments, with persistent cutaneous lesions.• Good response to IV rituximab. |
| Summary | 50% femaleMedian age, 65 years; range, 62–76 years | 75% cutaneous75% oral50% ocular25% nasal25% esophageal50% multisite involvementMedian disease duration, 4 years; range, 2–20 years | 50% linear IgG and C3 deposition25% linear IgG, IgA, and C3 deposition25% granular IgG, IgA, and C3 deposition | • IIF and salt-split skin IIF:○ 75% epidermal-side positivity○ 25% IgG, 25% IgA, and 25% both IgG and IgA• IB:○ 50% LAD-1 of BP180; 25% IgA and 25% IgG○ 25% IgG against integrin β4; 50% weak positivity○ 50% IgG against the BP180 NC16A domain• ELISA:○ 75% showed reactivity against BP180 | 50% multisite MMP 75% single-antigen involvement 75% IgG and IgA MMP 25% IgG MMP 100% anti-BP180 MMP; 50% LAD-1 and 50% NC16A 25% MMP with IgG antibodies against integrin β4 | 100% oral prednisone100% IV rituximab75% IV immunoglobulins75% oral dapsone75% cyclosporine50% SC methotrexate50% IV cyclophosphamide50% oral sulfasalazine25% mycophenolate mofetil | • 100% refractory to multiple lines of treatment.• 50% severe ocular involvement with cicatricial symblepharon.• 100% remission of ocular activity after cyclophosphamide, sulfasalazine, and rituximab.• 100% resolution of cutaneous and mucosal lesions after rituximab.• 75% cicatricial lesions. |
Summary of the results obtained after the circulating serum antibody study.
| Technique | Objective | Case #1 | Case #2 | Case #3 | Case #4 |
|---|---|---|---|---|---|
| IIF | Deposition on the epidermal cell membrane | IgG (−), IgA (−) | IgG (−), IgA (−) | IgG (−), IgA (−) | IgG (−), IgA (−) |
| IIF | Deposition on the epidermal basement membrane (anti-BMZ) | IgG (−), IgA (+) (up to 10×) | IgG (−), IgA (−) | IgG (−), IgA (±) (up to 10×) | IgG (−), IgA (−) |
| ss-IIF | Deposition on the epidermal side | IgG (−), IgA (+) (up to 10×) | IgG (−), IgA (−) | IgG (+), IgA (+) (up to 10×) | IgG (+) (up to 10×), IgA (−) |
| Deposition on the dermal side | IgG (−), IgA (−) | IgG (−), IgA (−) | IgG (−), IgA (−) | IgG (−), IgA (−) | |
| IB | IB of normal human epidermal extracts | Positivity detected | IgG (−), IgA (−) | Positivity detected | Positivity detected |
| IB for BP230 | IgG (−), IgA (−) | NS/NT | IgG (+), IgA (−) | IgG (−), IgA (−) | |
| IB for 210-kDa envoplakin | IgG (−), IgA (−) | NS/NT | IgG (−), IgA (−) | IgG (−), IgA (−) | |
| IB for 190-kDa periplakin | IgG (+), IgA (+) (may represent nonspecific reactivity, as normal serum also shows this band) | NS/NT | IgG (+), IgA (+) (may represent nonspecific reactivity, as normal serum also shows this band) | IgG (+), IgA (+) (may represent nonspecific reactivity, as normal serum also shows this band) | |
| IB for BP180 | IgG (−), IgA (−) | NS/NT | IgG (−), IgA (−) | IgG (+/−, very weakly), IgA (−) | |
| IB for Dsg1 (160-kDa PF antigen) | IgG (−), IgA (−) | NS/NT | IgG (−), IgA (−) | IgG (−), IgA (−) | |
| IB for Dsg3 (130-kDa PV antigen) | IgG (−), IgA (−) | NS/NT | IgG (−), IgA (−) | IgG (−), IgA (−) | |
| IB of RP of the NC16a domain of BP180 | IgG (−), IgA (−) | Weakly positive IgG (+), IgA NS/NT | IgG (−), IgA (−) | IgG (+), IgA (−) | |
| IB using RP of the C-terminal domain of BP180 | IgG (−), IgA (−) | IgG (−), IgA NS/NT | IgG (−), IgA (−) | IgG (−), IgA (−) | |
| IB of concentrated HaCaT cell culture supernatant (120-kDa LAD-1) | IgG (−), IgA (weakly +) | IgG (−), IgA NS/NT | IgG (+), IgA (−) | IgG (−), IgA (−) | |
| IB of normal human dermal extracts (290-kDa type VII collagen and p200) | IgG (−), IgA NS/NT | IgG (−), IgA (−) | IgG (−), IgA NS/NT | IgG (−), IgA NS/NT | |
| IB with RP of laminin 332 (165-kDa laminin α3, 135-kDa laminin β3, and 105-kDa laminin γ2) | IgG (−), IgA NS/NT | IgG (−), IgA NS/NT | IgG (−), IgA NS/NT | IgG (−), IgA (-) | |
| IB of hemidesmosome-rich (HD) fraction for anti-β4 integrin antibodies | IgG (−), IgA (−) | IgG: (+) for β4 integrin (INT), IgA (−) | IgG (±), IgA (−) | IgG (±), IgA (−) | |
| ELISA | BP180 ELISA | IgG NS/NT, IgA (−) (index 1.9, cutoff <9.0) | Index 11.8 (cutoff <9.0), weakly positive | IgG NS/NT, IgA (+) (index 38.9, cutoff >9.0) | IgG NS/NT, IgA (+) (index 60.9, cutoff >9.0) |
| BP230 ELISA | IgG NS/NT, IgA (−) (index 0.5, cutoff <9.0) | Index 4.8 (cutoff <9.0), Negative | IgG NS/NT, IgA (−) (index 0.3, cutoff <9.0) | IgG NS/NT, IgA (−) (index 8.5, cutoff <9.0) | |
| Dsg1 ELISA | IgG NS/NT, IgA (−) (index 0.2, cutoff <6.14) | Index 8.8 (cutoff <20.0), Negative | NS/NT | NS/NT | |
| Dsg3 ELISA | IgG NS/NT, IgA (−) (index 0.4, cutoff <20.0) | Index 12.0 (cutoff <20.0), Negative | NS/NT | NS/NT | |
| Type VII collagen ELISA | IgG NS/NT, IgA (−) (index 1.0, cutoff <20.0) | Index 3.7 (cutoff <6.14), Negative | IgG NS/NT, IgA (−) (index 0.1, cutoff <6.14) | IgG NS/NT, IgA (−) (index 1.6, cutoff <6.14) |
IIF, indirect immunofluorescence on normal skin and NaCl-split skin (ss-IIF); IB, immunoblotting; NS/NT, not specified/tested; RP, recombinant protein.
We found mucosal involvement similar to that described in the literature, with predominance of the oral mucosa, followed by ocular, nasopharyngeal, laryngeal, esophageal, and genital involvement. Three cases also presented cutaneous involvement, which is reported in the literature in 50% of cases.2–4
DIF is effective on both healthy and perilesional skin, with sensitivity ranging from 41% to 100%.1,5,6 Linear deposition of IgG and C3 is the most common immunoreactive pattern. Less frequently, IgA- and IgM-type autoantibodies may be found, either associated or isolated.1,7 The presence of IgA on DIF has been associated with a threefold increased risk of ocular involvement.3 Contrary to the literature, the two cases with positive IgA on DIF did not present ocular lesions, whereas the two cases without IgA did. However, one of them showed IgA antibodies in the serum study.
The sensitivity of conventional IIF is low: 35% with human skin and 85% with human mucosa. This is due to low titers and the heterogeneity of circulating autoantibodies.1 Sensitivity increases with ss-IIF, which identifies autoantibodies against epidermal antigens – BP180, BP230, and α6β4 integrin – in 60% of cases and against dermal antigens – laminin 332 and collagen VII – in up to 15%.3 Positivity on the dermal side has been associated with a greater number of affected sites, greater laryngeal involvement, and a greater need for rituximab.3 The combination of IgA and IgG, as well as the presence of positive IgG antibodies on ss-IIF, has been associated with treatment refractoriness.3,4 In our series, the sensitivity of the technique increased with the use of ss-IIF in three cases, all of which showed positivity on the epidermal roof. The case with a combination of IgA- and IgG-type autoantibodies was refractory to multiple treatments.
In our series, the study of specific autoantibodies by IB and ELISA showed results similar to those described in the literature: 3/4 [75%] vs 60% for a single antigen and 1/4 [25%] vs 40% for several antigens.3,9 The presence of antibodies against multiple domains has been associated with greater clinical severity.1,10 BP180 is the most frequent antigen and was present in all four of our cases.1,3,4 In addition to involvement of the NC16a domain of BP180, which is typical of bullous pemphigoid, MMP frequently shows involvement of deeper domains, such as LAD-1 and the C-terminal domain.4,9 The latter have been associated with greater mucosal involvement.9 The presence of IgA LAD-1 antibodies has been associated with a refractory course.3 In our series, the case of Brunsting-Perry MMP showed exclusive IgG NC16a antibodies, whereas the case with exclusive oral mucosal involvement showed IgG LAD-1. We highlight the second case, with exclusive IgA LAD-1 antibodies and severe, multirefractory ocular involvement.
Anti-BP230 antibodies are a rare finding, occurring in <2% of cases, and their pathogenicity in MMP has not been demonstrated.1,3 One of our cases showed weak positivity of uncertain significance.
The presence of antibodies against the β4 integrin subunit has been widely associated with ocular MMP.1 However, their detection is almost always associated with other autoantibodies, such as BP180, which may indicate epitope spreading rather than true pathogenicity.3 In our series, one case with severe ocular involvement showed strong positivity for IgG β4 integrin, associated with IgG BP180 (NC16a). Two cases without ophthalmological manifestations showed positivity of uncertain significance, whereas the other case of ocular MMP was negative.
The second most prevalent antigen, present in 35% of cases, is laminin 332.1 Its presence is associated with malignant diseases, occurring in one-third of cases, involvement of multiple sites – nasal and laryngeal – and greater use of rituximab.1–3 Finally, anti-collagen VII antibodies, the least frequent antibodies, occurring in <5% of cases, are associated with more frequent ocular involvement and a greater need for rituximab.3 None of our patients presented antibodies against these dermal antigens.
In conclusion, we describe the correlation between phenotype and specific autoantibodies in four cases of MMP, with results that were heterogeneous in some respects compared with the literature. This illustrates that, although this correlation may be useful in assessing disease severity, treatment, and monitoring, it is not perfect.
Conflict of interestThe authors declare no conflict of interest.
Uncited reference8.
The following are the supplementary data to this article:





