




 Artículo disponible en español
Hailey-Hailey disease (HHD) is a rare autosomal dominant genodermatosis characterized by blisters and erosions in skin folds, significantly impairing patients’ quality of life. HHD is caused by mutations in the ATP2C1 gene, which encodes the calcium transport protein SPCA1. Approximately 290 unique mutations have been identified to date; however, data remain scarce regarding mutations affecting patients in certain areas of Europe. The aim of this study was to analyze the ATP2C1 gene in a cohort of Spanish patients with HHD and to explore a possible genotype–phenotype correlation. We detected 10 mutations, including 9 unique variants, of which 6 were classified as likely pathogenic and 5 were novel. Additionally, we identified 3 novel variants of uncertain significance with a probable causal role. Our results expand the knowledge of genetic heterogeneity in European patients with HHD and identify new variants not previously reported.
Hailey-Hailey disease (HHD) is a rare genodermatosis with autosomal dominant inheritance and complete penetrance, characterized by blistering and crusted erosions in skin folds that significantly impair quality of life. The disease has a chronic recurrent course, with friction, heat, sweating, ultraviolet radiation, and microbial colonization acting as triggers and leading to exacerbations. Diagnosis is challenging, and in most cases there is a delay of several years.1
HHD is caused by mutations in the ATP2C1 gene (OMIM: 604384), which encodes the calcium (Ca2+) transport protein SPCA1. Misfolding or downregulation of this protein impairs Ca2+ sequestration, leading to depletion of Ca2+ in the Golgi lumen.1 Dysfunction of this protein also leads to errors in the synthesis and folding of proteins that constitute desmosomes, ultimately resulting in acantholysis.
Of note, the ATP2C1 gene is expressed in all tissues, although the clinical manifestations of HHD are observed only in the skin. This could be explained by the fact that SPCA1 is responsible for approximately 70% of Ca2+ trafficking in the epidermis but plays a less dominant role in other tissues.2,3
Traditionally, haploinsufficiency has been described as the primary cause of the disease, with the mutation affecting one gene copy while the remaining allele is insufficient to compensate.4,5 However, because approximately one-third of the 290 mutations described to date are missense variants, additional pathogenic mechanisms may also be involved.
Identifying new pathogenic variants can improve diagnosis, facilitate genetic counseling, and contribute to the development of targeted therapies. Recent reports have suggested that differences in clinical phenotypes may be more closely related to environmental factors than to the specific causative mutation.6 The objective of this study was to further characterize the genetic background of a Spanish cohort with HHD and to gain deeper insight into genotype–phenotype correlations.
MethodsTen probands of Spanish descent with biopsy-confirmed HHD lesions were included in this study. All patients provided written informed consent to participate, and the Institutional Review Board of our hospital approved the study (Ref. 2020.240).
DNA was extracted from peripheral blood samples anticoagulated with EDTA, and all coding exons and flanking regions of the ATP2C1 gene were analyzed using next-generation sequencing (NGS) with SeqCap EZ probes and the DNBseq-G400 platform (MGI Genomics). The databases used for variant classification were primarily ClinVar and ExAC. Variant classification followed the guidelines of the American College of Medical Genetics and Genomics7 (ACMG), as well as the VarSome and Franklin platforms.8
ResultsThe study included 10 patients, 6 women and 4 men, aged 37–81 years (mean age, 59 years; SD, 14). All patients had a family history of HHD and had presented skin lesions for at least 5 years. Among the participants, two were brothers (MB23524 and MB23523) and two were father and daughter (MB26619 and MB26618), whereas the remaining 6 patients were unrelated.
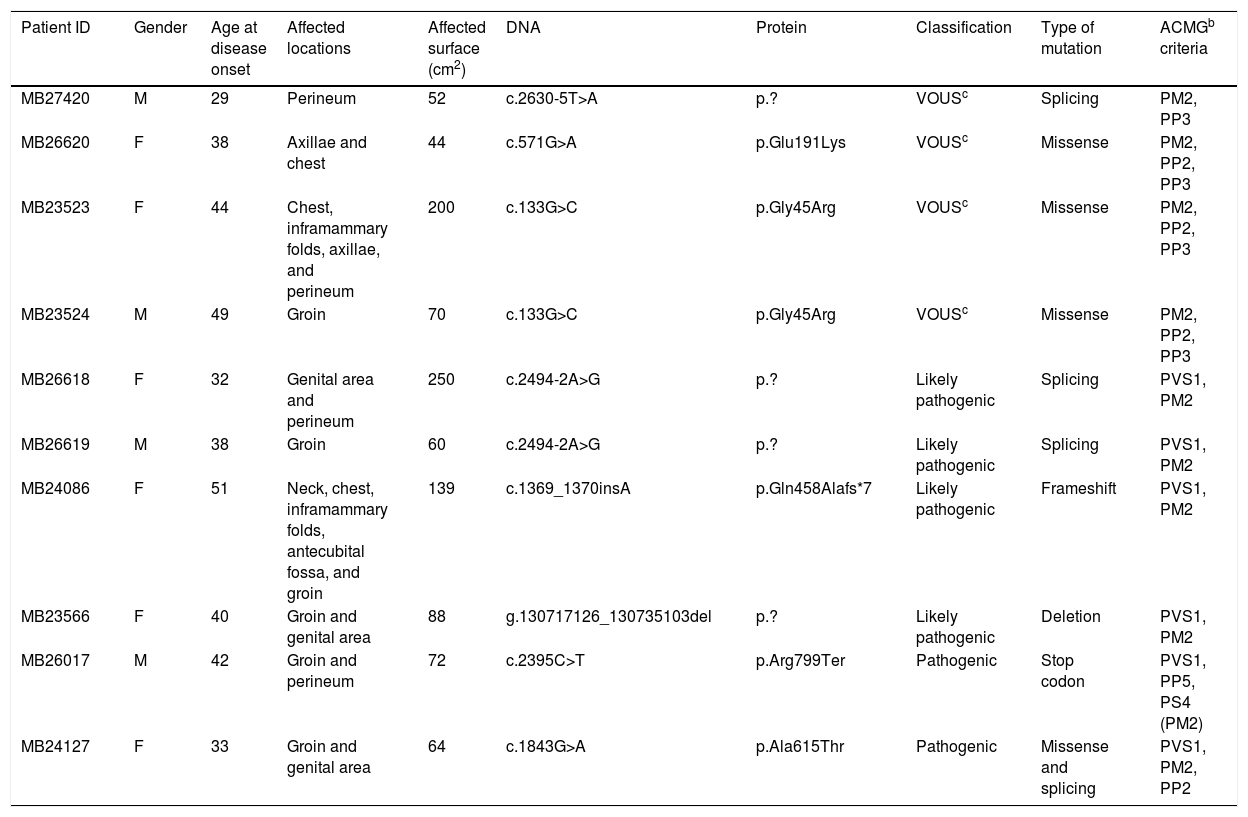
ATP2C1 variants were detected in all 10 probands and classified according to ACMG guidelines (Table 1). All variants except one (ID 1451141) were novel variants that had not previously been reported in publicly available databases. Notably, although the variants identified in patients MB26620 and MB23524/MB23523 were initially classified as variants of uncertain significance (VOUS) based solely on variant attributes, their classification was upgraded to likely pathogenic based on PP1 criteria (cosegregation with disease in multiple affected family members in a gene definitively known to cause the disease) and PP4 criteria (patient phenotype or family history highly specific for a disease with a single genetic etiology).
Characteristics and classification of the ATP2C1 mutations identified in Spanish patients with HHD.
| Patient ID | Gender | Age at disease onset | Affected locations | Affected surface (cm2) | DNA | Protein | Classification | Type of mutation | ACMGb criteria |
|---|---|---|---|---|---|---|---|---|---|
| MB27420 | M | 29 | Perineum | 52 | c.2630-5T>A | p.? | VOUSc | Splicing | PM2, PP3 |
| MB26620 | F | 38 | Axillae and chest | 44 | c.571G>A | p.Glu191Lys | VOUSc | Missense | PM2, PP2, PP3 |
| MB23523 | F | 44 | Chest, inframammary folds, axillae, and perineum | 200 | c.133G>C | p.Gly45Arg | VOUSc | Missense | PM2, PP2, PP3 |
| MB23524 | M | 49 | Groin | 70 | c.133G>C | p.Gly45Arg | VOUSc | Missense | PM2, PP2, PP3 |
| MB26618 | F | 32 | Genital area and perineum | 250 | c.2494-2A>G | p.? | Likely pathogenic | Splicing | PVS1, PM2 |
| MB26619 | M | 38 | Groin | 60 | c.2494-2A>G | p.? | Likely pathogenic | Splicing | PVS1, PM2 |
| MB24086 | F | 51 | Neck, chest, inframammary folds, antecubital fossa, and groin | 139 | c.1369_1370insA | p.Gln458Alafs*7 | Likely pathogenic | Frameshift | PVS1, PM2 |
| MB23566 | F | 40 | Groin and genital area | 88 | g.130717126_130735103del | p.? | Likely pathogenic | Deletion | PVS1, PM2 |
| MB26017 | M | 42 | Groin and perineum | 72 | c.2395C>T | p.Arg799Ter | Pathogenic | Stop codon | PVS1, PP5, PS4 (PM2) |
| MB24127 | F | 33 | Groin and genital area | 64 | c.1843G>A | p.Ala615Thr | Pathogenic | Missense and splicing | PVS1, PM2, PP2 |
aHuman Genome Variation Society.
bAmerican College of Medical Genetics and Genomics.
Although a genotype–phenotype correlation has not yet been established, notable observations were made among related patients in our series.
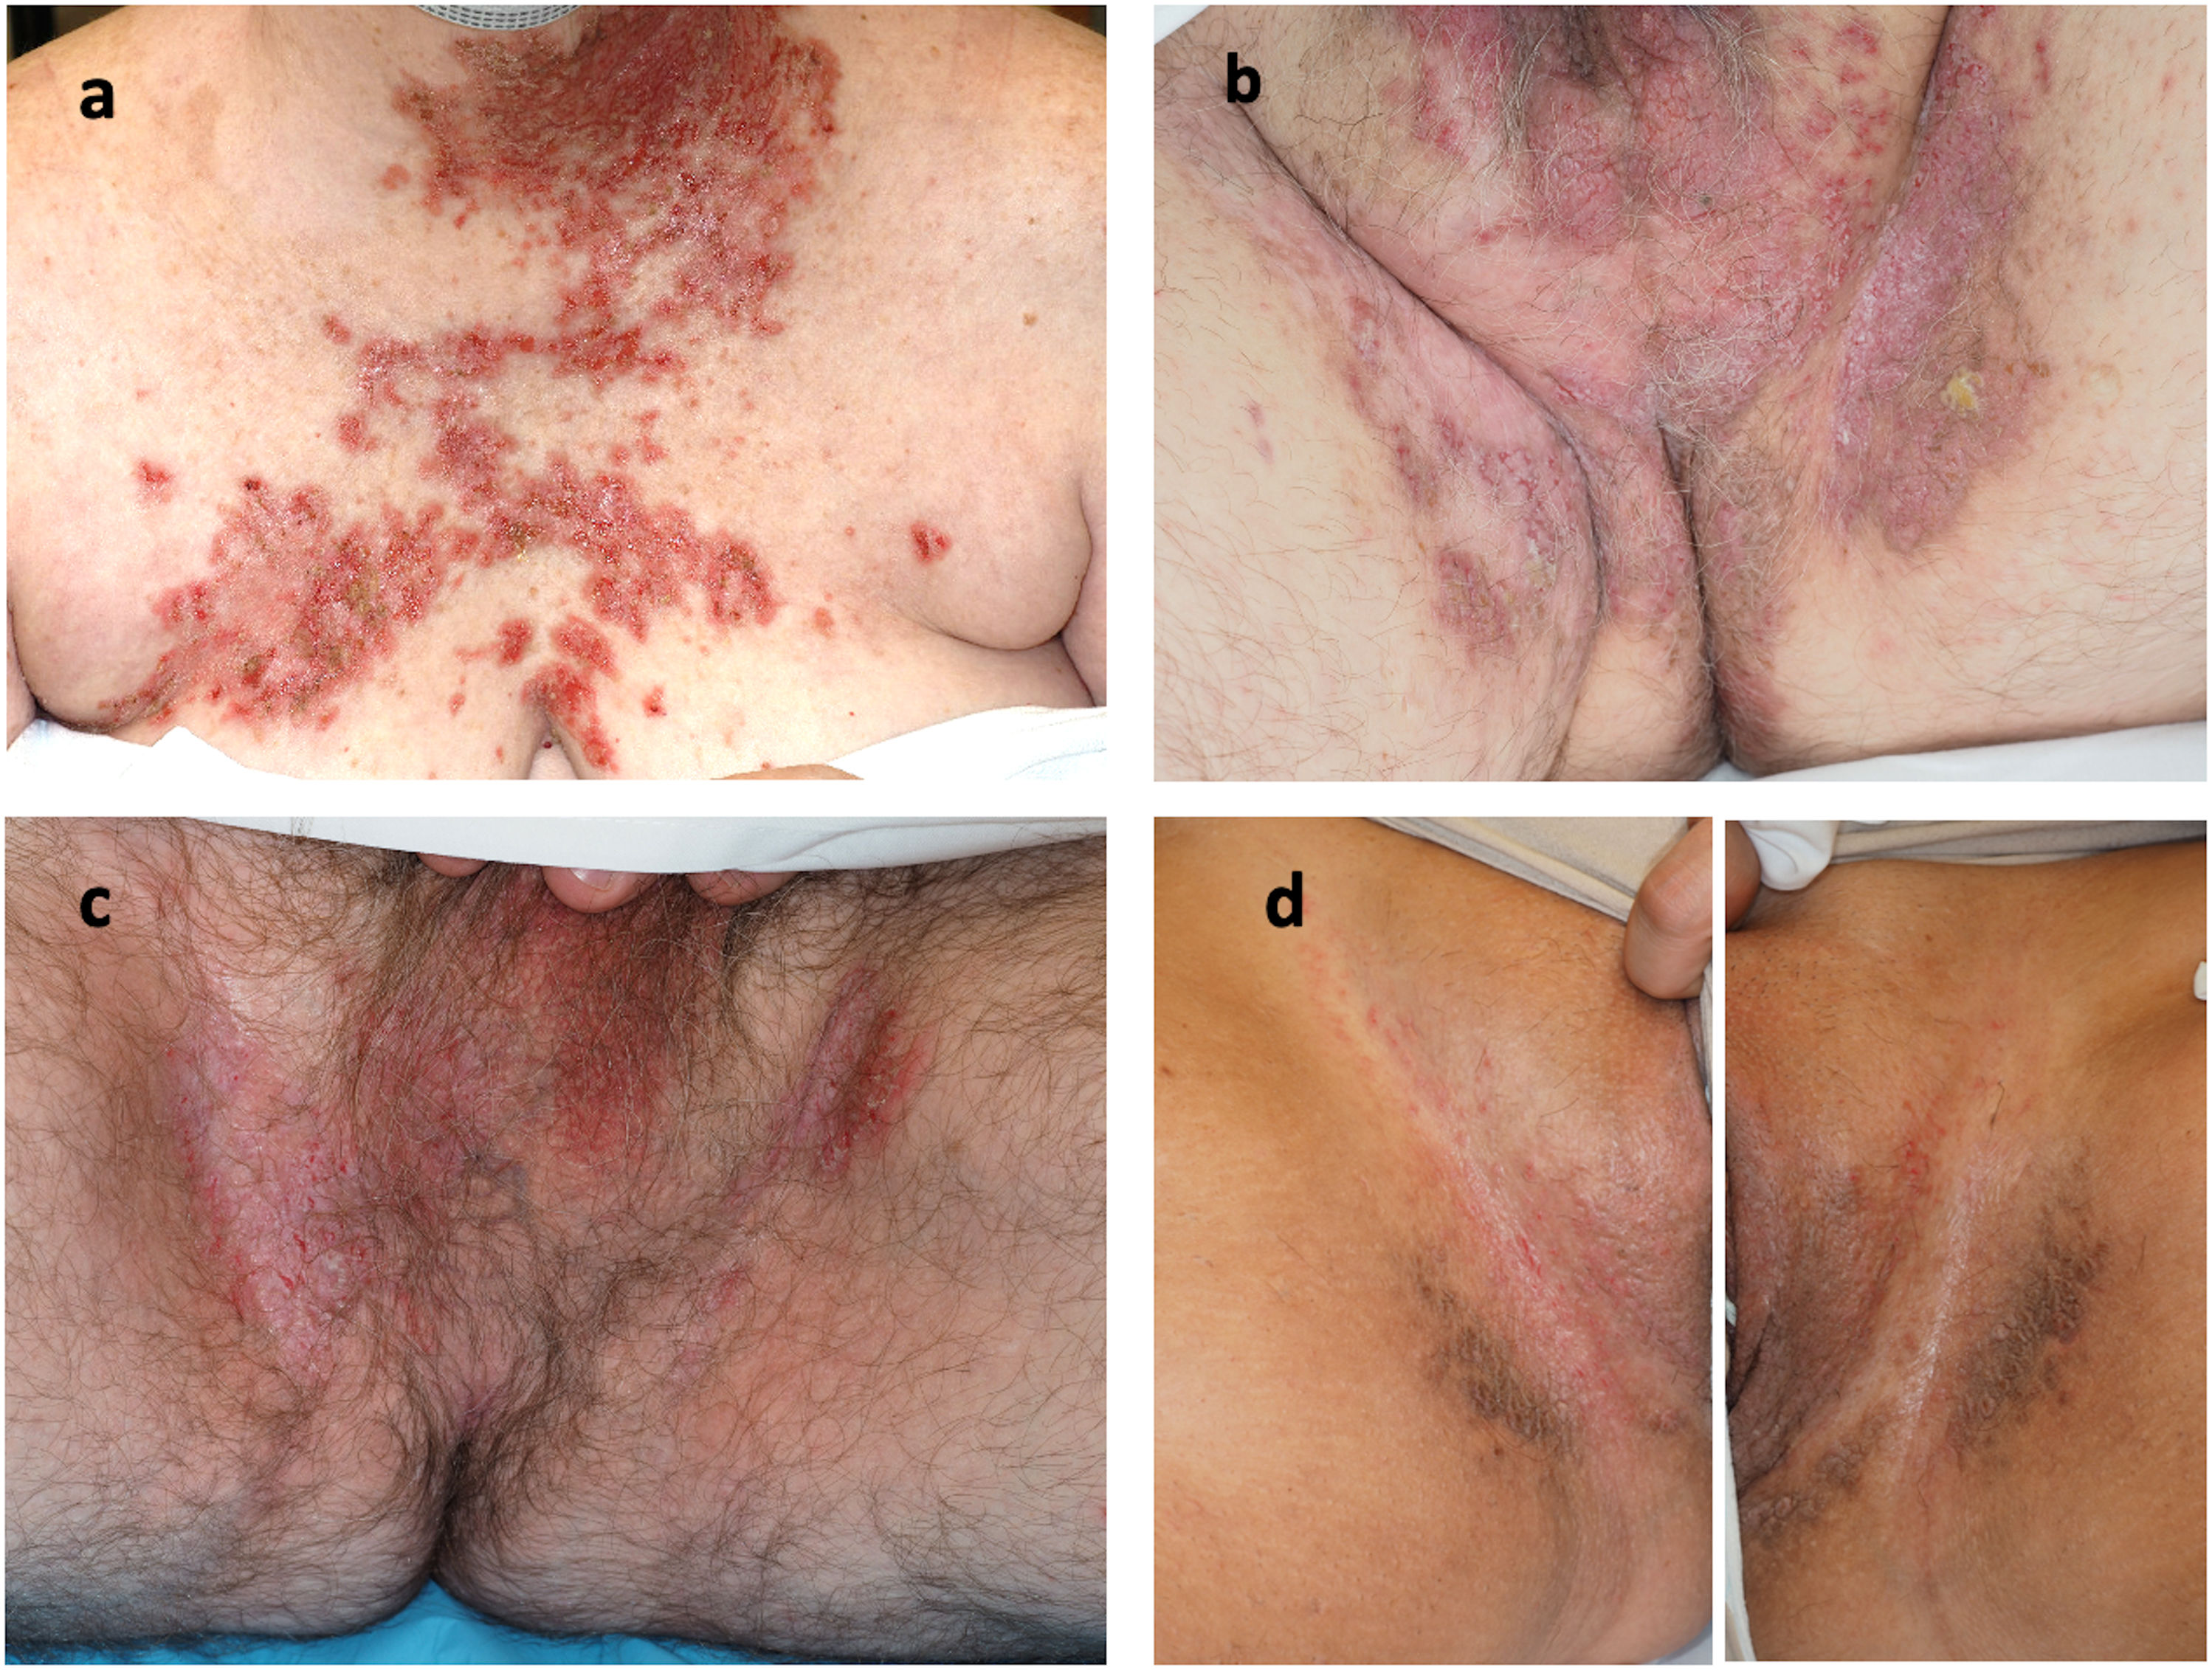
Patients MB23524 and MB23523, who were brothers, carried the same VOUS in exon 3 but exhibited markedly different clinical severities. Patient MB23523 presented an active lesion area of 200cm2 involving the chest, submammary folds, axillae, and perineum, whereas patient MB23524 had an active lesion area of 70cm2 limited to the groin.
Similarly, in the father-daughter pair (MB26619 and MB26618) carrying a splicing mutation in exon 24, there was a substantial difference in clinical presentation. The father exhibited 250cm2 of active disease involving the genital area and perineum, whereas the daughter presented only 60cm2 of affected skin limited to the groin (Fig. 1).

Active lesions of Hailey-Hailey disease in related patients included in the series. Patient MB23523 presented erythematous plaques with erosive areas on the chest, covering an area of 200cm2 (A). Patient MB26619 presented erythematous plaques in the groin covering an area of 250cm2 (B). Patient MB23524, brother of MB23523, presented lesions in the groin covering an area of 70cm2 (C). Patient MB26618, daughter of MB26619, presented lesions in the groin covering an area of 60cm2 (D).
Among the remaining unrelated patients in the series, the mean affected area was 75cm2 (SD, 41), and no association was identified between the extent of disease and the genetic variants.
DiscussionMultiple mutations have been reported in the ATP2C1 gene, including 35% missense variants, 2.6% in-frame mutations, 12.6% splice-site alterations, 14.3% nonsense mutations, 21.2% frameshift mutations resulting in a premature stop codon, and 13.7% variants without coding impact or located in noncoding regions. The classical molecular theory of disease suggests that HHD is caused by haploinsufficiency; however, other investigators have proposed a dominant-negative effect as the primary pathogenic mechanism.1,7
In the present study, we identified several variants classified as likely pathogenic or pathogenic, including variants associated with altered splicing, deletions, premature stop codons, and frameshift mutations that may result in an abnormally truncated SPCA1 protein. Nonsense-mediated decay (NMD) or endoplasmic reticulum–mediated protein degradation may substantially reduce protein expression levels, whereas partial splice and frameshift mutations may damage the structural and functional domains of SPCA1, affecting its cellular localization or activity.8,9 Additionally, we identified 3 novel variants of uncertain significance (VOUS) located in exons 3, 8, and 18. Nevertheless, the identification of these VOUS in an HHD-associated gene, together with their occurrence in patients with clinical phenotypes and histologic findings consistent with those observed in patients harboring known pathogenic variants (PP4 criteria), suggests probable pathogenicity. Furthermore, one of these variants was identified in two affected brothers and another in an affected father and daughter, supporting a potential causal role in disease development (PP1 criteria).
To date, no VOUS variants have been described in exon 3 of ATP2C1. However, missense mutations in exon 8 have been reported to cause structural alterations in the SPCA1 protein, leading to abnormal protein folding or destabilization of correctly folded SPCA1.10 Similarly, missense mutations in exon 18, which encodes the ATP-binding domain within the transmembrane region, have been described as critical for Ca2+ binding. Although the precise mechanisms by which VOUS lead to HHD remain unclear and cannot always be predicted using current computational algorithms, recent studies suggest that these variants may alter SPCA1 expression levels or disrupt ion transport through modifications of catalytic cycle reactions.11 Specifically, such variants may not affect the cellular localization of SPCA1 but may reduce its expression and enzymatic activity, thereby impairing Ca2+ transport rates. In addition, some missense mutations may produce structural alterations in SPCA1 despite maintaining normal mRNA expression levels.11
The identification of novel missense mutations indicates considerable genetic diversity within this population. However, despite the heterogeneity of molecular alterations, the functional consequences of these mutations appear to produce similar phenotypic outcomes.
It has also been suggested that external factors, in addition to genetic mutations (multifactorial inheritance), may contribute to the HHD phenotype. Variable clinical severity has been reported among family members carrying the same mutation, as observed in our series.12 These findings suggest that even with different genetic alterations the resulting protein dysfunction may be comparable, and conversely, identical mutations may lead to distinct clinical phenotypes.
ConclusionsWe report new findings regarding ATP2C1 mutations in a cohort of Spanish patients with HHD, including 5 novel variants classified as likely pathogenic and 3 novel VOUS with a probable causal role. These findings expand the current understanding of the genetic basis of HHD and may contribute to reducing diagnostic delay while facilitating genetic counseling.
Ethical disclosuresThe Institutional Review Board of the hospital approved this study, and the guidelines of the Committee on Publication Ethics (COPE) were followed.
FundingThis project was funded by the State Research Agency (Spain) (reference PID2020-114340RA-I00).
Conflicts of interestAll authors involved in this manuscript declare no conflicts of interest, including financial interests, activities, relationships, or relevant affiliations.




