




Protothecosis is a rare infection caused by algae of the genus Prototheca, which comprises P. wickerhamii, P. zopfii, P. stagnora, P. ulmea, and P. blaschkeae; of these, the first 2 cause disease in humans.1 These algae are saprophytes found, among other environments, in soil, rivers, animal waste, and decaying plants, although domestic animals may also be carriers.2
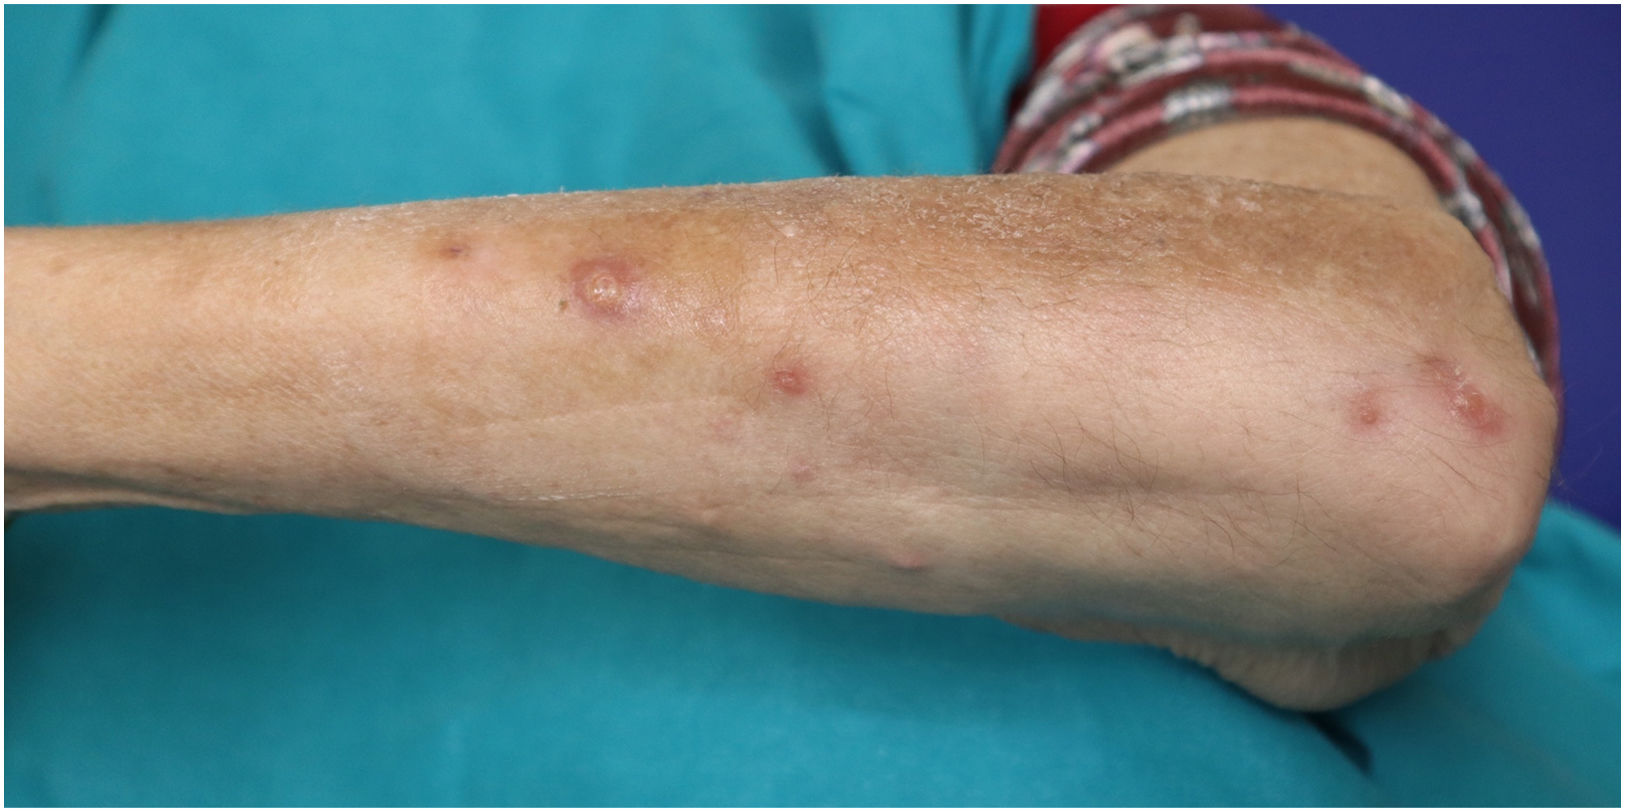
A 74-year-old woman with hypertension and dyslipidemia, who had been on hemodialysis for chronic kidney disease for 6 years, was referred to the dermatology department because of ulcerative nodular lesions located on the left forearm—the same arm in which she had an arteriovenous fistula—and distributed in a sporotrichoid pattern, with a 2-month history (Fig. 1). Microbiological cultures performed by the nephrology department had tested negative.

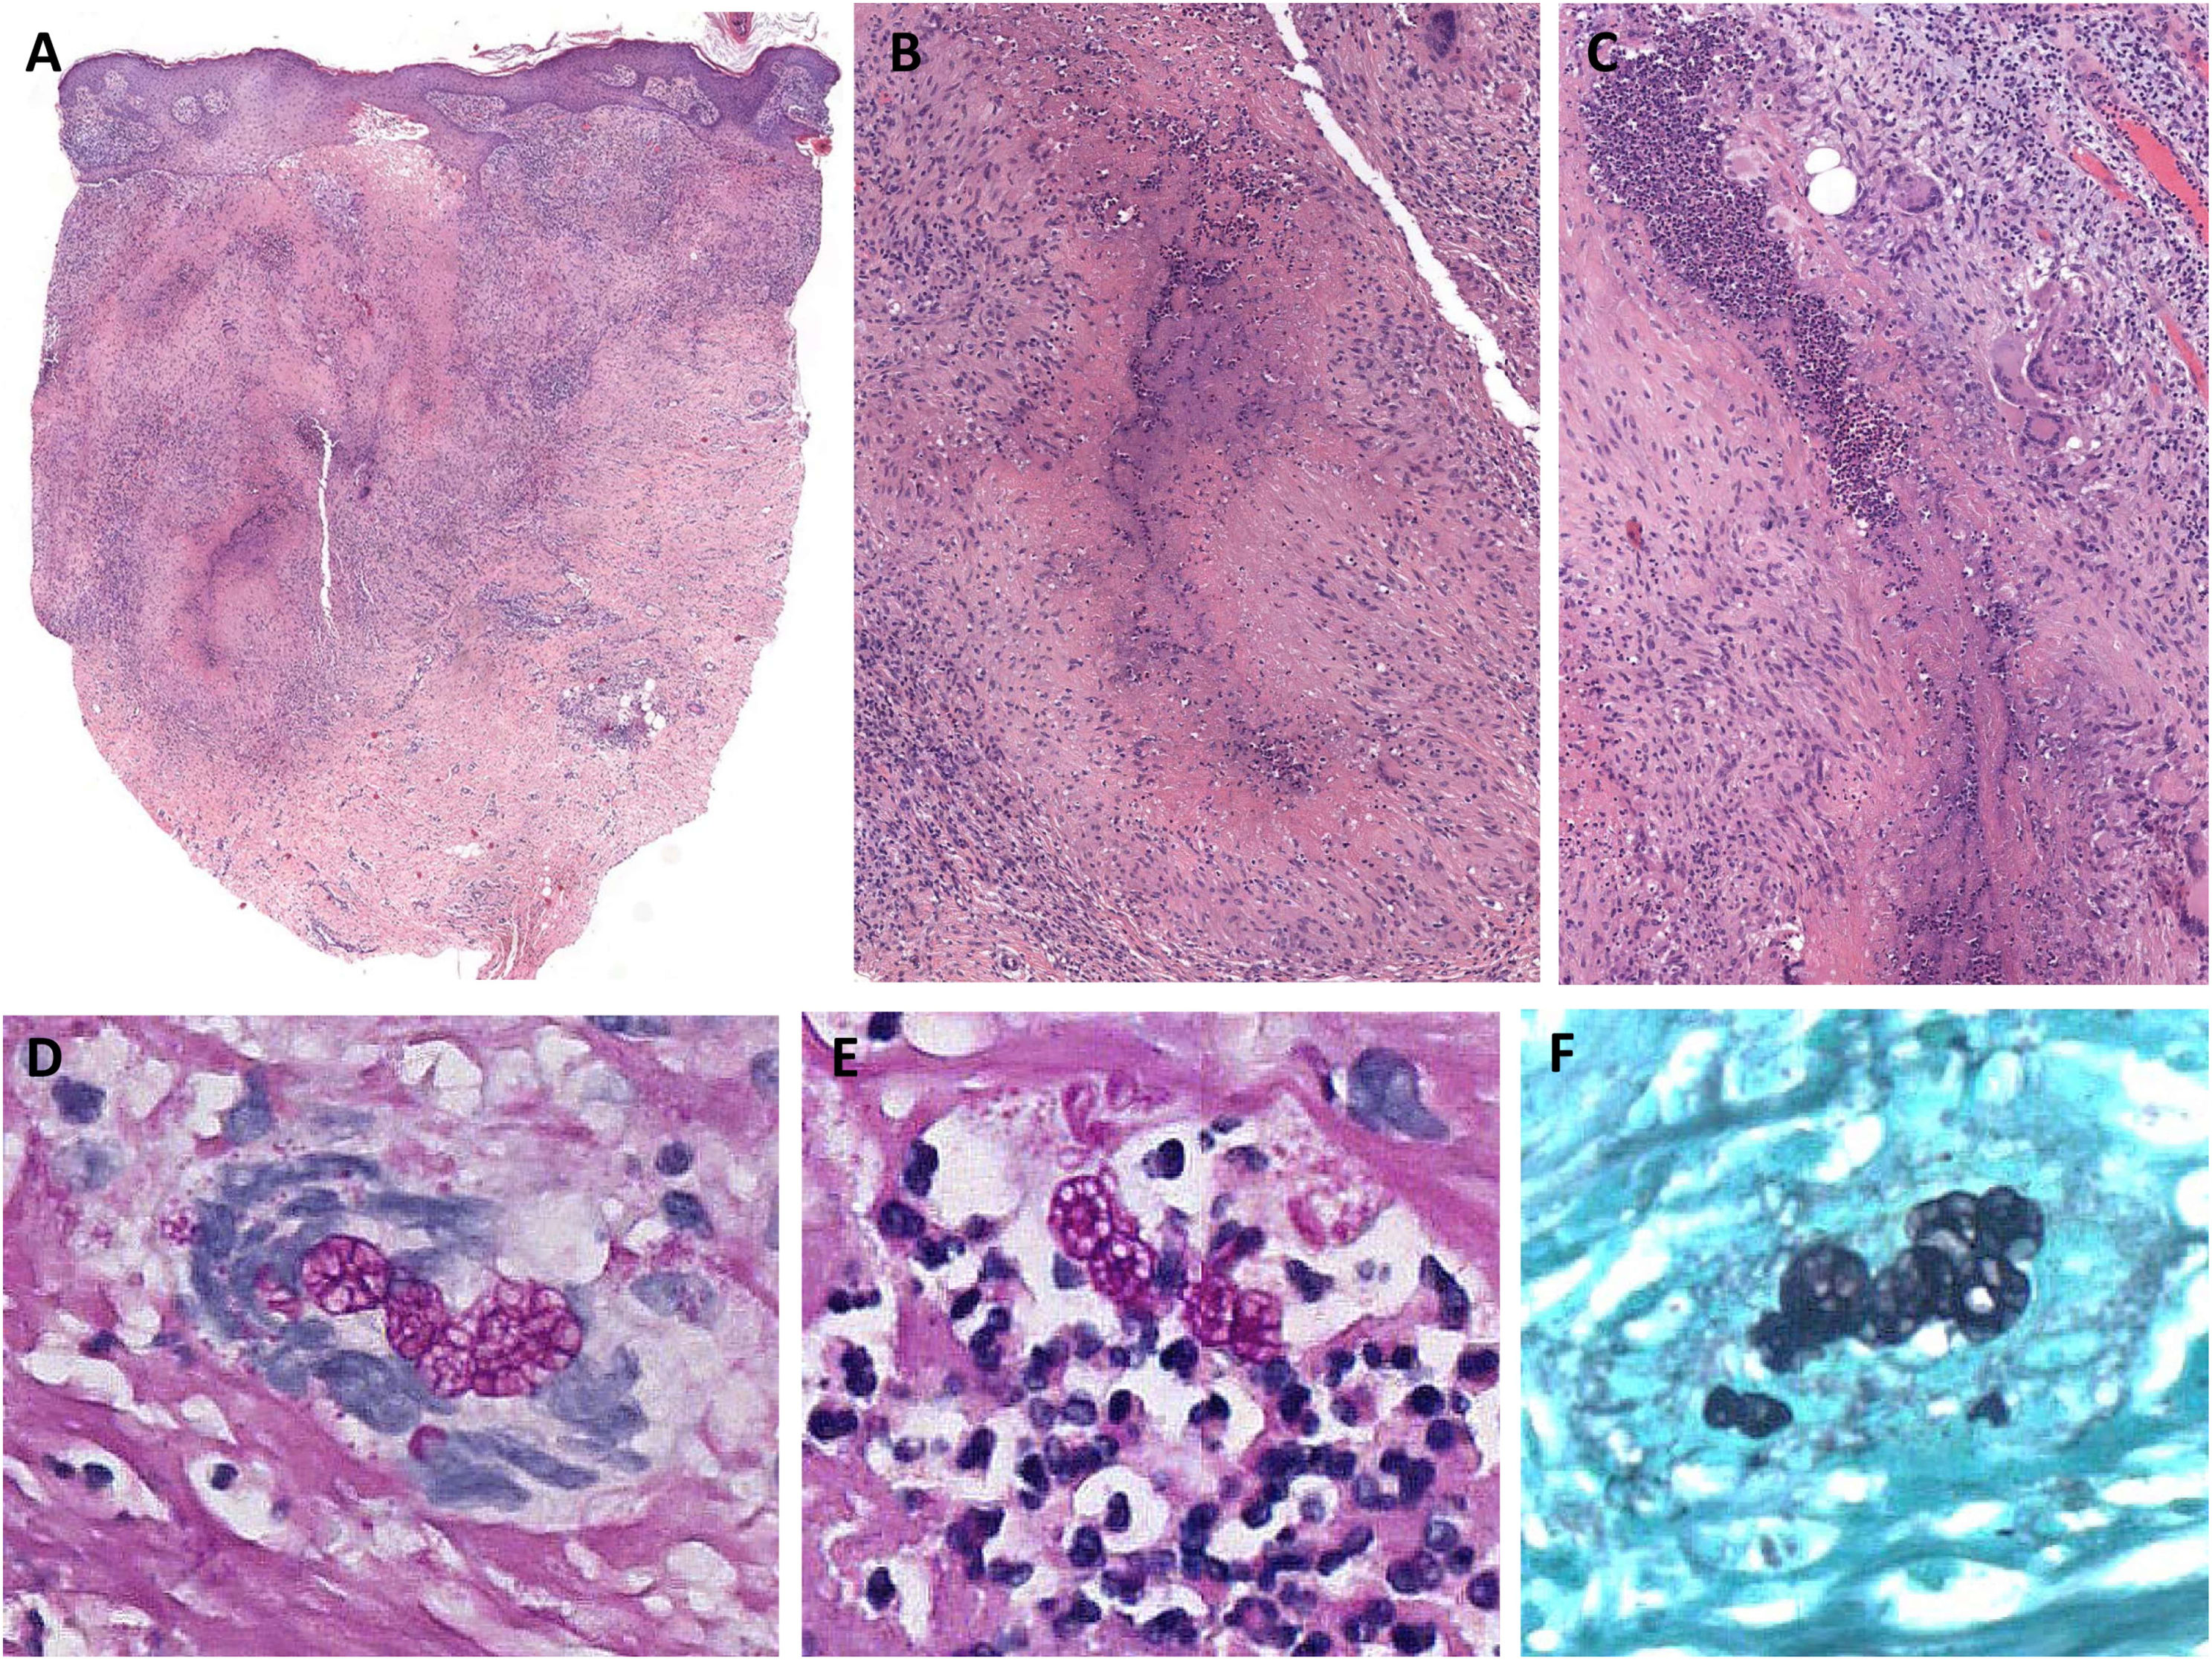
A punch biopsy was performed with the clinical suspicion of dystrophic calcification in the context of the patient's chronic hemodialysis status and the recurrent nature of the lesions, with a tendency toward ulceration and subsequent resolution. Histological analysis showed areas of epidermal and infundibular pseudoepitheliomatous hyperplasia accompanied by follicular granulomatous inflammation with necrosis and abscess formation, as well as epithelioid cells and multinucleated giant cells (Fig. 2A–D). To rule out a fungal infection, Grocott and periodic acid–Schiff (PAS) histochemical stains were performed, revealing characteristic morula-like structures corresponding to sporangia produced by Prototheca infection. These were located both inside multinucleated giant cells and in necrotic and abscessed areas (Fig. 2D–F). In our case, given the morphology of the sporangia, the infection was probably caused by P. wickerhamii.

Clinically, protothecosis may be localized or systemic, with cutaneous and subcutaneous forms being the most frequent. It has a variable presentation, including ulcerative vesiculobullous lesions, erythematous plaques, papules, nodules, or verrucous lesions.3 Another frequent form of involvement is olecranon bursitis.4 In humans, inoculation may originate from plants, fish, or seafood,5 so occupations such as gardening or fishmongering may be considered risk factors. Inoculations after surgical procedures have also been reported,6 which raises the possibility that, in our case, the infection may have originated from repeated hemodialysis, taking into consideration the coincidence in lesion location. In addition, dialysis has been described as a possible risk factor, together with diabetes, cancer, alcoholism, and HIV infection.5
Diagnosis can be established by culture, molecular testing, or histology,7 the latter being highly characteristic because it shows rounded unicellular organisms with internal endospores—sporangia—that stand out because of their morula-like appearance and are associated with suppurative granulomatous inflammation.8
Although the method of choice for confirming the pathogenic subtype within the genus Prototheca is molecular testing or culture, histology can also help distinguish between infection caused by P. wickerhamii and P. zopfii. The former usually shows a circular morphology with symmetrically arranged internal endospores, as in our case, whereas the latter is characterized by larger size, oval or cylindrical morphology, and an asymmetric arrangement of the septa of the internal endospores.7
Currently, fewer than 200 cases of protothecosis have been published,7 predominantly in tropical areas, countries with a high degree of humidity, and some African countries,9 with very few cases reported in Spain.10
The case described illustrates the need to consider cutaneous protothecosis in the differential diagnosis of recurrent ulcerative lesions, especially in patients with diabetes and in those undergoing dialysis.
FundingNone declared.
Conflicts of interestNone declared.




